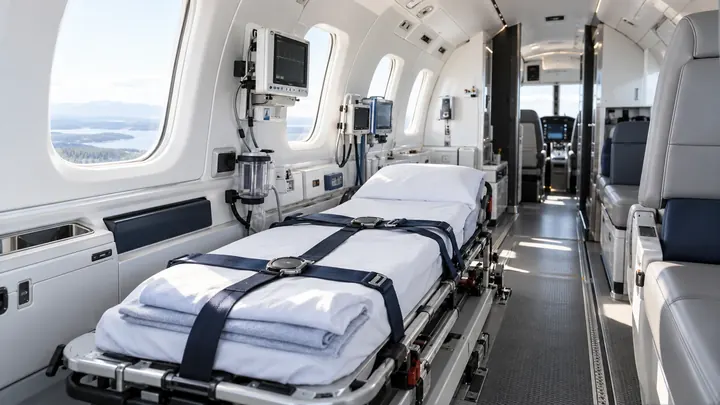
A healthcare coordination platform can connect more organisations while making responsibility for patient information harder to follow. Before an investor evaluates features or geographic expansion, the project should show what information it needs, who may see it and how it supports continuity of care. A clear boundary around clinical records is part of the service design.
Begin with the decisions information supports
A referring clinician, transport team, receiving provider and billing function have different information needs. Map those needs to actual tasks rather than giving everyone access to a complete patient file. The clinical team should determine the information required for safe assessment and handover; administrators should receive the information appropriate to their responsibilities.
WHO's data principles emphasise privacy and careful handling of sensitive medical information. Those principles govern WHO's own data work; they provide a useful reference rather than a substitute for the rules applicable to a particular service.
Maintain a usable handover record
Protecting information must be compatible with its availability to authorised care teams. The service should explain how the current referral and transfer record reaches the next provider, how corrections are communicated and who confirms receipt. WHO's transfer tools connect documentation with the other tasks required for coordinated movement.
An investor can ask for a demonstration using fictional patient data. Follow an amended referral from the sending team through dispatch to the destination and examine whether each authorised participant receives the appropriate version.
Decide access and custody before integration
The project needs a written allocation of responsibilities among participating providers and technology suppliers. It should address access approval, retention, incident response, subcontractors and what happens when a partnership ends. Cross-border plans require assessment of the actual data flows and applicable obligations before connections are activated.
These are questions for qualified providers and advisers in the intended jurisdictions. A platform's technical ability to exchange a record does not settle whether an organisation is authorised to collect or use it.
Keep public reporting away from identifiable cases
Sponsors may want to demonstrate progress through mission stories and operating metrics. Establish a review process that considers whether small groups, dates, routes or clinical details could reveal a person's identity even after names are removed. Public reporting should be designed for its purpose rather than copied directly from operational records.
The ALFA whitepaper explicitly states that sensitive health information should not be treated as public token or marketing data. A proposed digital utility layer does not create a reason to expose clinical records to a public ledger.
Treat the information model as a launch dependency
ALFA’s healthcare programme needs information boundaries aligned with its provider agreements before patient data enters a service workflow. A reviewable milestone would combine a data-flow map, approved access roles, partner responsibilities and a tested handover process. Demonstrating those foundations would give a prospective purchaser more useful assurance than showing a polished referral interface without an agreed model for the records behind it.